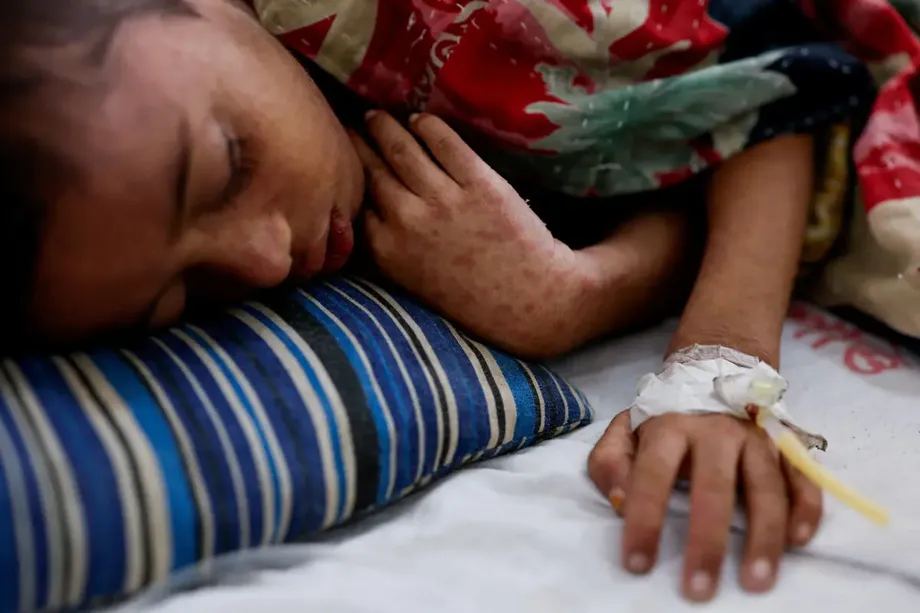
Healthcare costs erode gains against poverty
More than 10.8 million people in Bangladesh were pushed below the poverty line by medical payments in 2022, according to a Health Economics Unit study presented in Dhaka on October 28, 2026. That was 6.4% of the population, compared with 5.6 million people, or 3.9%, in 2005. An academic analysis of the same national survey year estimated a smaller toll of 6.13 million people, or 3.7%.
Contents
- Healthcare costs erode gains against poverty
- What the different measures mean
- How the academic study counted medical poverty
- Medical spending has grown beyond inflation
- The poorest families face the greatest pressure
- Rural households and Barishal bear heavier burdens
- Medicines and changing patterns of care
- Public funding is reaching poorer people less effectively
- Later household findings show little room for another bill
- Key Points
The government study, Financial Risk Associated with Out-of-Pocket Healthcare Payments and Benefit Incidence in Bangladesh, was conducted with support from the World Health Organization and the Swedish Embassy. It examined four rounds of the Household Income and Expenditure Survey, known as HIES, covering 2005, 2010, 2016 and 2022.
Bangladesh's national poverty rate fell from 40% in 2005 to 18.7% in 2022. Yet the number pushed into poverty by healthcare expenses nearly doubled over those years. The finding exposes a weakness in that progress: a family can earn enough to meet everyday needs and still lose its financial footing when someone becomes ill.
The Health Economics Unit also found that 41.7% of people faced financial hardship from healthcare spending in 2022, up from 28.2% in 2005. The 2022 figure exceeded the global estimate of 26% by 15.7 percentage points.
Medicines, diagnostic tests, hospital stays and consultation fees were major contributors. For households with little money left after food, housing and other necessities, paying for treatment meant having less available for those same basic needs.
What the different measures mean
Out-of-pocket payments are costs that people pay directly for healthcare rather than having them covered by the government, insurance or another payer. They include spending on medicines, consultations and tests.
The Health Economics Unit measured financial hardship when medical payments exceeded 40% of the money remaining after basic needs had been met. It also measured catastrophic health expenditure using a different threshold: medical spending above 10% of total household consumption. Consumption means the goods and services a household uses, measured through its expenditure.
Under that second measure, the government study found that catastrophic spending rose from 12.5% in 2005 to 32.1% in 2022. The academic analysis estimated 17.72% of households at the same 10% threshold. Its estimates were 7.07% at a threshold of 25% of total consumption and 9.46% at a threshold of 40% of spending excluding food.
Each threshold asks a different question about a household's budget. Measuring spending after basic needs focuses on the money a family has left to spare. Measuring a share of total consumption compares medical costs with its entire budget. Poverty estimates then ask whether the resources remaining after medical bills fall below a minimum level needed for daily life.
How the academic study counted medical poverty
Researchers Abdur Razzaque Sarker, Rasedul Islam and An Tran-Duy examined 14,395 households in their BMJ Open study, Catastrophic health expenditures and medical impoverishment in Bangladesh: evidence from the Household Income and Expenditure Survey. Their analysis used HIES 2022 and a poverty line of Tk 3,832 per person per month.
The researchers compared household consumption before and after deducting medical payments. Their estimated poverty headcount rose from 19.01% to 22.71%, an increase of 3.70 percentage points. They estimated that about 1.35 million households crossed below the poverty line after healthcare costs were deducted.
The study converted household findings into population estimates using survey weights and household size, with an estimated national population of 166.9 million. For treatment without an overnight hospital stay, spending covered the preceding 30 days. For hospital admissions, it covered the preceding 12 months.
The precise reasons for the gap between the government and academic estimates have not been reconciled publicly in the findings described here. Their calculations of poverty, spending and household resources require a direct methodological comparison.
The academic researchers also identified a gap in what spending surveys can capture: their catastrophic expenditure analysis excluded people who needed care but could not afford to seek it. Household recall and reporting could also affect the recorded costs.
Medical spending has grown beyond inflation
Average monthly household payments rose from Tk 1,241 in 2005 to Tk 3,238 in 2022 in the Health Economics Unit study. Those amounts were adjusted for inflation, meaning the increase reflects a greater financial burden after allowing for the changing value of money.
The increase was Tk 1,997 a month, or about 161%. Over the same period, the share of households reporting any direct medical payment rose from 52.5% to 92.7%, a rise of 40.2 percentage points. Healthcare expenses had become part of the budget for almost every household.
The academic study reported average monthly spending of Tk 1,904 across all households and Tk 3,454 among households that incurred medical expenses. Those averages describe different groups: including families that recorded no spending brings the average down.
The BIDS research page on inequality in urban and rural medical costs cites a World Bank estimate that households directly pay nearly 74% of Bangladesh's healthcare costs. The Bangladesh Institute of Development Studies project is directed by Sarker, a research fellow, and lists funding from REF, BIDS.
BIDS also cites approximately 18% of households facing catastrophic expenditure and the academic estimate of medical impoverishment. Its research agenda focuses on who needs care, who pays and how the burden differs between rural and urban households.
The poorest families face the greatest pressure
Financial hardship affected 90.8% of people in the poorest fifth of the population ranked by consumption in 2022, according to the Health Economics Unit. Among the richest fifth, the rate was 13.6%. That is a gap of 77.2 percentage points.
Subrata Paul, the unit's focal point for Universal Health Coverage and National Health Accounts, described the unequal burden at the presentation.
"The poorest households were the worst sufferers," he said.
A small medical bill can take a large share of the money left in a poor household's budget. Wealthier families may spend more in taka while retaining enough for food, housing and other essentials. The hardship measure captures that difference in ability to pay.
The academic study identified greater exposure to catastrophic spending among larger families, households with elderly members, people seeking treatment for chronic illnesses and those using hospital care. Repeated treatment matters because the expense returns each month, while a hospital admission can create a large bill at once.
The studies describe families meeting medical expenses through borrowing, savings, help from relatives or selling and mortgaging assets. Those choices can extend the pressure beyond the period of illness: money used for treatment is no longer available for another emergency, and loans require repayment.
Rural households and Barishal bear heavier burdens
Rural residents faced a financial hardship rate of 47.9% in 2022, compared with 28.2% in urban areas, the government study found. The rural rate was 19.7 percentage points higher.
Barishal experienced the sharpest reversal highlighted in the findings. Its hardship rate was 22.5% in 2005, the lowest among Bangladesh's divisions. By 2022, it had risen to 59.1%, the highest.
Barishal's increase of 36.6 percentage points was much larger than the national rise of 13.5 percentage points. The figures give policymakers a reason to examine where financial protection is weakest rather than relying only on a national average.
Earlier research also documented unequal exposure, although it measured catastrophic expenditure rather than the newer hardship indicator. A study using HIES 2010 found catastrophic spending in 16.5% of the poorest households and 9.2% of the richest. At the 10% threshold, its national estimate was 14.2%, and it estimated that medical payments pushed 5.1 million people into poverty.
The sequence of findings spans several survey years:
- 2005: The Health Economics Unit estimated 5.6 million people were pushed into poverty by medical payments.
- 2010: An academic analysis estimated 14.2% of households faced catastrophic spending at the 10% threshold.
- 2016: Public facilities provided 61.3% of inpatient care, while pharmacies accounted for 32.5% of outpatient care.
- 2022: The government study recorded higher financial hardship and growing reliance on pharmacies and private inpatient care.
- October 28, 2026: The Health Economics Unit findings were presented in Dhaka.
Medicines and changing patterns of care
Medicines accounted for 64.6% of direct medical spending in expenditure data cited by the BMJ Open paper. Laboratory charges represented 11.7% and consultation fees 10.8%. Together, those three categories accounted for 87.1%.
Medicine costs therefore sit at the centre of the affordability problem. The government's study recommended free and reliable access to essential medicines and diagnostic services, alongside continuous, affordable care for chronic conditions.
Pharmacies also became a much larger source of outpatient care. Their share rose from 32.5% in 2016 to 55.4% in 2022, an increase of 22.9 percentage points. By 2022, they accounted for more than half of such care in the government's findings.
Public facilities remained the largest provider of inpatient treatment, but their share fell from 61.3% to 56% between 2016 and 2022. Private providers increased their share from 36.9% to 42.5%.
For families, these changes place greater weight on the cost of medicines and the fees charged where they receive treatment. For public services, the practical task includes making essential supplies available consistently so that patients can receive the treatment those services are meant to provide.
Public funding is reaching poorer people less effectively
The Health Economics Unit found that the distribution of benefits from public healthcare spending had become less favourable to poorer households than in 2016. Its assessment of inpatient care raised concerns about whether public resources were reaching people with the greatest health and financial needs.
Public spending can protect a family when it pays for treatment that would otherwise come from the household budget. The distribution of that benefit matters alongside the amount spent: poorer families have less capacity to replace a missing medicine or pay for a diagnostic test privately.
The study recommended increasing public financing, improving the efficiency and fairness of spending, and restoring a stronger flow of public healthcare benefits to poorer people. The academic researchers proposed prepayment arrangements, including national health insurance, to protect households against large bills.
Prepayment means contributing to a shared fund before illness occurs, through arrangements such as taxes or insurance. The fund then helps pay for care when someone needs it, spreading costs across people and time rather than leaving an individual family to meet the bill immediately.
State Minister for Health MA Muhit expressed concern at the presentation and said the government was committed at the highest level to curbing irregularities and corruption in the health sector. He also blamed conditions under the Awami League government. The recommendations concern financing, access and the distribution of services as well as the administration of funds.
Later household findings show little room for another bill
Bangladesh's newer household research describes how thin the financial cushion has become. A Power and Participation Research Centre survey of 8,067 households in May 2025 found average monthly income of Tk 32,685 and expenditure of Tk 32,615, leaving only Tk 70.
At the October 17, 2026 presentation of those findings, medical bills were identified as triggers for 67.4% of financial crises. The findings on household financial fragility also placed about 31 million people in a vulnerable group at risk of falling into poverty after illness, lost earnings or another shock.
The poorest 40% spent more than they earned, while only 27.5% of households classified as vulnerable but not poor received safety net support. That combination makes the proposed protection concrete: affordable medicines, dependable public treatment and support with recurring costs could leave more money available for food and other necessities.
The 2022 health expenditure findings and the later household survey both describe families with limited capacity to absorb illness. The policy challenge is to reduce the bill at the point of care while directing public resources towards people who have the least room to pay.
Key Points
- The Health Economics Unit estimated that medical payments pushed more than 10.8 million Bangladeshis into poverty in 2022; an academic analysis estimated 6.13 million.
- The government study found financial hardship affected 41.7% of people, up from 28.2% in 2005.
- Hardship affected 90.8% of the poorest consumption group and 47.9% of rural residents.
- Medicines were the largest spending category in expenditure data cited by the academic study.
- Recommendations include more public financing, reliable essential medicines and diagnostics, affordable chronic care and shared financing arrangements.